What's Actually Being Made — the Modality Landscape
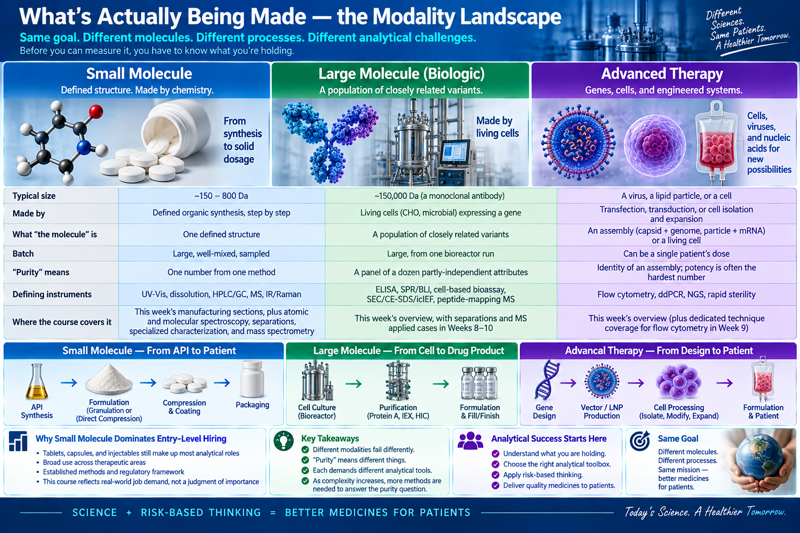
Before any technique week makes sense, the course needs to answer what is actually being made: a small molecule, a large molecule / biologic, and an advanced therapy compared side by side — size, manufacture, what “the molecule” even is, what purity means, and why small molecule dominates entry-level hiring.
Before the course can teach how you measure something, it has to teach what you are holding — a small molecule, a large molecule, and an advanced therapy fail differently, are made differently, and demand entirely different definitions of “pure.”
What’s actually being made — the modality landscape
Before any of the technique weeks make sense, the course needs to answer a question that has to come first: what is actually being made?
The bottom rows are a thread the whole course pulls on: as a modality gets more complex, the “purity” question needs more methods to answer it, and each of those methods has to work harder to defend its own answer.
How each modality is made and tested
Small molecule — API synthesis and scale-up, then solid-dosage manufacturing (direct compression vs. granulation, compression, coating, packaging). Dissolution — the one routine test about the patient’s experience rather than the molecule’s identity — is covered later, in Week 9, alongside the other characterization techniques. The technique weeks that measure all of this — atomic spectroscopy, molecular spectroscopy, separations, specialized characterization, mass spectrometry — follow later in the term.
If you walk into a QC or analytical-development lab in this industry, the odds are strongly in favour of small molecule: tablets, capsules, and injectables built from defined organic synthesis still dominate the number of open analytical roles, which is why this course gives that column the most technique-week time and the other two their own depth here, up front, instead of spread across dedicated weeks. That is not a judgment about which modality matters more scientifically — it is a plain reflection of where the jobs are, and a course meant to get you ready for one should weight itself the same way.
Source note. The modality landscape follows standard pharmaceutical-technology and biopharmaceutical references; the jobs-market framing follows industry hiring-volume reporting (BioSpace, ACS C&EN annual employment surveys) rather than a single citable guideline. (Instructor: confirm current hiring-volume figures if citing numbers in lecture.)
1 - How an API Is Made — Synthesis and Scale-Up
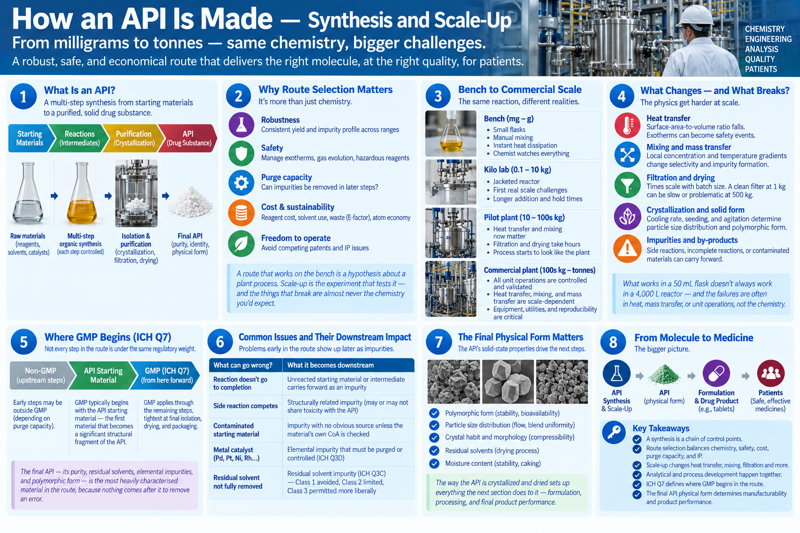
The active pharmaceutical ingredient as a multi-step organic synthesis: route selection, why bench chemistry and plant chemistry are different disciplines, what changes — and what breaks — going from milligrams to tonnes, where ICH Q7 GMP begins in the route, and how the API’s final physical form sets up everything the next section does to it.
Before there is a tablet, there is a molecule, and before there is a molecule at commercial scale, someone has to have proven — repeatedly, at increasing scale — that the same reaction that worked in a 50 mL flask still works in a 4,000 L reactor. That proof is process research and scale-up, and it is where most of an API’s eventual impurity profile and physical form get decided.
The one idea
A route that works on the bench is a hypothesis about a plant process. Scale-up is the experiment that tests it — and the things that break are almost never the chemistry you’d expect.
A synthesis is a chain of control points
An API is built from starting materials through a defined sequence of reactions, each producing an isolable intermediate, until the final step delivers the API itself — usually followed by a purification (crystallization, sometimes chromatography) that fixes its final form. Every step is a place where things can go right or wrong:
What can go wrong at a step
What it becomes downstream
Reaction doesn’t go to completion
Unreacted starting material or intermediate carries forward as an impurity
A side reaction competes
A structurally related impurity, sometimes sharing the API’s toxicity, sometimes not
A contaminated or off-spec starting material
An impurity with no obvious source unless the material’s own CoA is checked
A metal catalyst (Pd, Pt, Ni, Rh…)
An elemental impurity that has to be purged or controlled — the direct link to ICH Q3D testing, the week atomic spectroscopy is taught
Residual reaction solvent not fully removed
A residual solvent impurity (ICH Q3C), classed by toxicity (Class 1 avoided, Class 2 limited, Class 3 permitted more liberally)
None of this is visible in the finished white powder. It is found — or missed — by the analytical methods built around the route, which is why route chemistry and analytical method development happen together, not in sequence.
Choosing a route is not just chemistry
Process research doesn’t take the first route that works; it evaluates candidate routes against criteria that have nothing to do with whether the reaction is elegant:
Robustness — does the yield and impurity profile hold up across the ranges of temperature, concentration, and reagent quality a plant will actually see, or does it need bench-level precision?
Safety — exotherms, gas evolution, unstable intermediates, reagents that are fine in a fume hood and dangerous in a jacketed reactor holding hundreds of litres.
Purge capacity — can later steps (crystallizations especially) reliably wash an impurity out, so an early imperfection doesn’t have to be perfect?
Cost, atom economy, and green chemistry — solvent volumes, reagent cost, waste generated per kilogram of API, and increasingly a formal E-factor target.
Freedom to operate — does the route avoid a competitor’s process patent?
A route redesigned late in development to fix one of these is common, and every redesign reopens the impurity and degradation picture — which is exactly the “moving target” that makes a systematic, comparable analytical program non-negotiable across route changes.
Bench → kilo lab → pilot plant → commercial plant
The same reaction run at four scales is not the same experiment, because the physics around the chemistry changes with vessel size in ways the flask never revealed:
Scale
Typical batch
What’s now different
Bench
mg – g
Fast manual mixing, instant heat dissipation, chemist watches every addition
Kilo lab
0.1 – 10 kg
First real jacketed reactor, first agitator design, first taste of longer addition and hold times
Pilot plant
10 – 100s kg
Heat transfer and mixing efficiency now scale-dependent, not assumed; filtration and drying take hours, not minutes
Commercial plant
100s kg – tonnes
Every unit operation (charge, react, quench, extract, crystallize, filter, dry) is now a controlled, validated process step
Why scale-up breaks things that bench chemistry never revealed:
Surface-area-to-volume ratio falls as vessels get bigger, so heat that dissipated instantly in a flask now has to be removed through a jacket — an exotherm that was a non-event on the bench can become a runaway or a safety incident in a reactor.
Mixing and mass transfer get harder, not easier — a reagent added over seconds by hand goes in over hours through a dip pipe, so local concentration and temperature gradients appear that a flask never had, changing selectivity and impurity formation.
Filtration and drying times scale with cake depth and batch size, not linearly with batch mass — a crystallization that filters cleanly at 1 kg can be impractically slow, or dry unevenly, at 500 kg.
Crystallization control becomes the whole ballgame for the API’s final physical form — cooling rate, seeding, and agitation at scale determine particle size distribution and polymorphic form, both of which the next section inherits directly: they decide whether the API even flows and compresses well enough for direct compression, or whether it needs granulating first.
Where GMP begins in the route
Not every step in the synthesis is manufactured under the same regulatory weight. ICH Q7 draws a line at the API starting material — the raw material or intermediate that becomes a significant structural fragment of the API — and GMP applies from that point forward, tightening as the route approaches the final isolation. The logic is purge capacity again: an error early in the route can still be removed by a later purification step; an error in the final crystallization, drying, or micronization reaches the patient with nothing left to catch it. This is also why the final isolated API — its purity, its residual solvents, its elemental impurities, its polymorphic form — is the single most heavily analytically characterised material in the whole route.
Where the analyst sits
The chemist who ran the route on the bench is rarely the person defending it in a regulatory filing five years later at commercial scale. The record that survives — validation batches, in-process specifications, impurity qualification data — has to speak for a process that changed as it scaled. Reading that record and asking does this impurity limit still make sense given how the route actually runs today is analytical judgment, not chemistry.
For discussion
A palladium-catalysed coupling step is three steps before the final API isolation. Why might the elemental-impurity risk still be considered high, even with two purifications in between?
A crystallization that gave a single, reproducible polymorph at kilo-lab scale gives a mixture of two polymorphs at pilot-plant scale, with no change to the recipe on paper. What changed, and how would you find out?
Process research chooses a lower-yielding route because it avoids a Class 1 residual solvent entirely. Was that the right trade, and what would change your answer?
Source note. Route selection and scale-up follow standard process-chemistry texts (Anderson, Practical Process Research & Development) and the Q3C residual-solvent classes. GMP scope follows ICH Q7. (Instructor: add a specific worked route once course examples are finalised.)
2 - From Powder to Tablet — Solid-Dosage Manufacturing
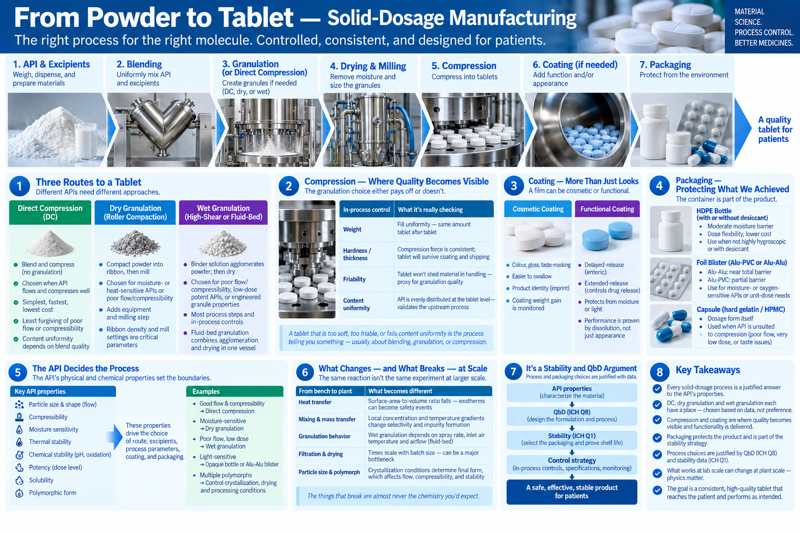
Turning the API powder into a tablet the patient can swallow: direct compression versus dry (roller-compaction) and wet (fluid-bed) granulation, compression and coating, and the packaging that protects what all of it achieved — bottles, foil blisters, and capsules — with each process choice justified against the API’s own properties and the stability / quality-by-design case behind it.
The previous section ended with the API’s final physical form — particle size, flow, compressibility, moisture sensitivity — decided by how it was crystallised and isolated. Everything in this section is downstream of that: the API’s own properties decide which manufacturing route is even available, before a single formulation decision is made.
The one idea
Every solid-dosage process is a justified answer to one question: given what this API actually is — how it flows, how it compresses, what degrades it — what is the least-handling route to a tablet that still meets its specification, batch after batch?
Three routes to a tablet, in order of how much they touch the powder
Route
What happens
When it’s chosen
What it costs you
Direct compression (DC)
API and excipients blended, then compressed straight into tablets — no intermediate agglomeration step
The API already flows and compresses well at the required dose; the simplest, cheapest, fastest route
Least forgiving of a poorly flowing or poorly compressible API; content uniformity is entirely dependent on blend quality
Dry granulation (roller compaction)
Powder is compacted into a ribbon between rollers, then milled into granules
API is moisture- or heat-sensitive, or doesn’t flow/compress well enough for DC, but can’t tolerate wet processing
Adds equipment and a milling step; ribbon density and mill settings become new critical parameters
Wet granulation (high-shear or fluid-bed)
A binder solution or suspension agglomerates the powder into granules, which are then dried
Poor flow or compressibility, low-dose potent APIs that need better content uniformity, or where granule properties must be engineered
Adds a drying step (moisture must come back out); the most process steps, the most in-process controls, the most that can go wrong
Fluid-bed granulation is the wet route worth naming specifically: the powder bed is fluidised in a stream of air while binder solution is sprayed in, and the granules are dried in the same vessel without transferring the batch — one piece of equipment doing agglomeration and drying together, which reduces handling but makes airflow, spray rate, and inlet-air temperature the parameters that decide whether the granule comes out right.
Compression and the properties it exposes
Whichever route produced the material — powder blend or granules — it is compressed into tablets, and compression is where the granulation choice either pays off or doesn’t:
In-process control
What it’s really checking
Weight
Fill uniformity — is the die filling the same amount, tablet after tablet?
Hardness / thickness
Compression force is consistent, and the tablet will survive coating and shipping
Friability
The tablet won’t shed material in handling — a proxy for how well the granulation held together
Content uniformity
The API is evenly distributed at the tablet level, not just the blend level — the test that ultimately validates the whole upstream route
A tablet that is too soft or too friable is usually a granulation problem revealing itself late; a tablet with poor content uniformity is usually a blending or flow problem revealing itself even later still. Compression is the first point any of this becomes visible as a number.
Coating — cosmetic, or a control
A film applied to the compressed tablet does one of two different jobs:
Cosmetic / taste-masking — colour, gloss, ease of swallowing, identity (colour and imprint) for the patient and pharmacist. Coating weight gain is tracked, but performance isn’t riding on it.
Functional coating — delayed-release (enteric, survives the stomach) or extended-release (controls the rate the drug is available at all). Here the coating is the mechanism, and dissolution becomes the test that decides whether the product works, not just whether it looks right.
Packaging — protecting what the process just achieved
Everything upstream — the API’s stability, the tablet’s moisture sensitivity, whether the coating is intact — is only as good as the container that ships it:
The API is not highly hygroscopic or photosensitive, or a desiccant closes the gap
Foil blister (Alu-PVC or Alu-Alu)
Alu-Alu is close to a total moisture/oxygen barrier; Alu-PVC is a partial one
Alu-Alu for genuinely moisture- or oxygen-sensitive APIs; Alu-PVC where the risk is lower and unit-dose presentation still matters
Capsule (hard gelatin / HPMC)
The dosage form itself, packaged in bottle or blister
The API is unsuited to compression at all — poor compressibility, very low dose needing a carrier, or a taste that tableting can’t mask
The justification is a stability and QbD argument, not a preference
None of the choices above are made on convenience. Each is defended with data and traced back to a control strategy:
The route (DC vs. dry vs. wet granulation) is justified by the API’s measured flow, compressibility, and moisture/heat sensitivity — a quality-by-design argument under Q8: the process is designed around the material’s known properties so that a conforming batch is the expected outcome, not a hoped-for one.
The packaging is justified directly by stability data under ICH Q1 — a hygroscopic API that shows significant change in an open-dish humidity study earns an Alu-Alu blister or a desiccant bottle; a photosensitive one earns an opaque bottle or overwrap, backed by Q1B photostability data.
Container-closure integrity is itself a tested attribute, not an assumption — it is part of what the stability program is confirming batch after batch, on the shelf, for the life of the product.
Put together, the manufacturing route and the pack are two halves of one answer to the same question this week’s risk-management framework asks of everything it touches: what could go wrong with this specific molecule, and what does the process or the pack have to do about it?
Where the analyst sits
None of the choices above are visible in a finished tablet by inspection. A tablet made by direct compression and one made by wet granulation can look identical and perform very differently under stress — which is exactly why the in-process controls in the tables above exist, and why a batch record reader needs to know which control is protecting against which upstream decision.
For discussion
A roller-compacted formulation and a wet-granulated formulation both meet release specifications for the same product. What stability or robustness question would you still want answered before picking one for commercial launch?
An API is reformulated from a bottle with desiccant to an Alu-Alu blister after a stability failure. What does that change tell you about the API, and what data would have predicted it before the failure?
A functional (extended-release) coating passes every appearance and weight-gain check, but the batch still fails dissolution. Where would you look first?
Source note. Solid-dosage unit operations follow standard pharmaceutical-technology texts (Aulton, Pharmaceutics: The Design and Manufacture of Medicines). QbD justification follows ICH Q8; packaging justification follows ICH Q1.
3 - How the Toolkit Scales Up — Large Molecules & Biologics
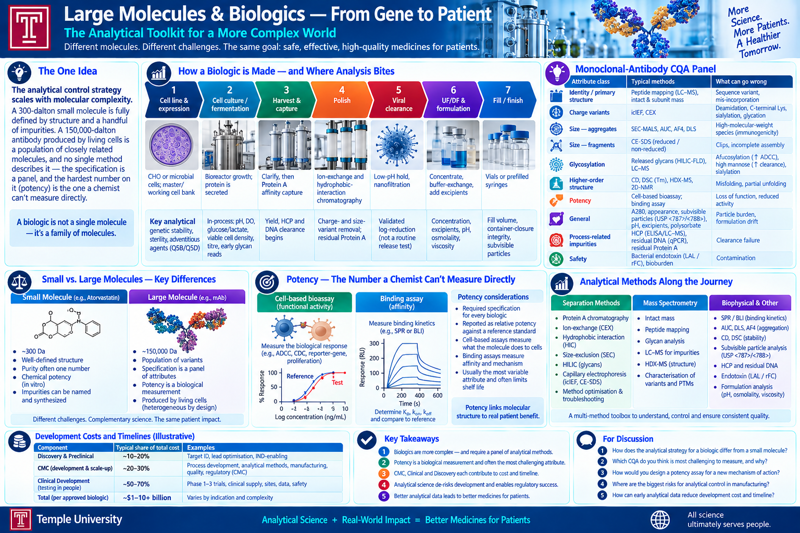
How the analytical toolkit scales up to biologics: recombinant manufacture and the control points along it, the monoclonal-antibody CQA panel, potency as a biological measurement, binding kinetics by SPR/BLI, particles and aggregation, and comparability (ICH Q5E) — the large-molecule column of the modality landscape, in depth.
This section fills in the large molecule column of the modality landscape table above. A small molecule’s “purity” is one number from one method; a protein’s is a dozen partly-independent attributes, and its potency is a biological measurement, not a chemical one. The separations and mass-spectrometry methods that read most of this panel are taught in full — with a worked case that starts here — in Separation Methods and Mass Spectrometry.
The one idea
The analytical control strategy scales with molecular complexity. A 300-dalton small molecule is fully defined by structure and a handful of impurities. A 150,000-dalton antibody produced by living cells is a population of closely related molecules, and no single method describes it — the specification is a panel, and the hardest number on it (potency) is the one a chemist can’t measure directly.
How a biologic is made — and where analysis bites
Step
What happens
Analytical control
Cell line & expression
A gene inserted into CHO (or microbial) cells; a master/working cell bank
Fill volume, container-closure integrity, subvisible particles
Contrast with small-molecule manufacturing: defined reactions, isolable intermediates, impurities you can name and synthesise. Here the “impurities” are the cells’ own proteins and DNA, and the product itself is heterogeneous by design.
The monoclonal-antibody CQA panel
Attribute class
Methods
What can go wrong
Identity / primary structure
Peptide mapping (LC–MS), intact & subunit mass — taught in full
Potency is a required specification for every biologic, and usually the one that limits shelf life. It is a biological measurement of function, reported as relative potency against a reference standard:
Cell-based bioassays — proliferation, reporter-gene, ADCC/CDC — measure what the molecule does to cells, often read out by flow cytometry (counting labelled cells or measuring a fluorescent reporter one cell at a time — Week 9 teaches the technique in full; the advanced-therapies section introduces its CAR-T application). Biologically relevant, and variable: geometric %CV of 10–20% is normal.
Binding assays — ELISA, and kinetic methods (SPR / Biacore, BLI / Octet) measuring association and dissociation rate constants and affinity (KD) — are more precise but measure binding, not function; acceptable when binding is shown to predict activity.
The reference standard is itself a stability-limited material with a potency value; when it is replaced, a bridging study re-anchors the scale, and any drift there propagates into every future result.
Particles and the immunogenicity link
Protein aggregates and subvisible particles are associated with immunogenicity. Control spans three size regimes with different methods, and no single method covers the range: submicron (DLS), subvisible ~1–100 µm (light obscuration, flow imaging microscopy), and soluble oligomers (SEC, AUC, AF4). Orthogonality is the theme: you believe an aggregation result when methods with different failure modes agree.
Comparability — the analytical argument
Every manufacturing change — a new site, a bigger bioreactor, a formulation tweak — raises the question: is it still the same product?ICH Q5E answers it with a tiered, risk-based analytical comparison: the more an attribute matters to safety and efficacy, the more sensitive the method and the tighter the acceptance criterion. Biosimilars run the same logic in reverse: analytical similarity to the reference product is the foundation of the whole abbreviated pathway.
Worked case — a charge-variant shift after a process change
A mAb process moves to a larger bioreactor. Post-change lots show acidic charge variants up from 18% to 26% by icIEF. Everything else in the panel is comparable, and potency is unchanged. Peptide mapping localises the extra acidic species to increased deamidation at a known site; HDX-MS and an FcRn binding assay confirm it doesn’t affect binding or recycling. The resolution: comparable on function, a localised and characterised chemical difference within prior experience, accepted with a tightened in-process control. Had potency moved, or had the variant been uncharacterised, it would have needed a PK bridging study.
Where the analyst sits
With a panel this large, the judgment is triage — which attribute is the one that would actually harm a patient if it drifted. And potency forces a specific call the rest of the course doesn’t: how much assay variability is acceptable when the attribute is function itself. That is the STEAM “A” at its most consequential.
On the job
A large-molecule CQA panel report will land on your desk as a dozen numbers from a dozen instruments — your first real skill is triage: which one, if it drifted, would you refuse to release on?
Expect your first exposure to potency assays to be as a reader of a bioassay report, not a runner of one — cell-based assays are typically run by a specialized team, but every analyst on the product needs to interpret the %CV and the reference-standard bridging history.
“Comparable” on a Q5E comparability exercise is a conclusion you’ll be asked to defend line by line, attribute by attribute — not a single yes/no you can wave at.
For discussion
A mAb’s potency assay has a geometric %CV of 18%. The specification is 80–125% relative potency. How many replicates do you need to make a confident release decision, and what does that cost per batch?
SEC says 2.0% aggregate; AUC says 3.5%. Which do you report, and how do you resolve the discrepancy?
In the worked case, what would have made you insist on a PK bridging study despite unchanged potency?
Biosimilar developers argue analytical methods are now sensitive enough to make some comparative clinical trials unnecessary. Where is that argument strong, and where does it break?
Source note. Manufacturing and control follow standard biopharmaceutical references and ICH Q5A–Q5E, Q6B, and Q11. Potency and bioassay design follow USP ⟨1032⟩–⟨1034⟩; particles follow USP ⟨787⟩/⟨788⟩/⟨1787⟩. Comparability follows ICH Q5E; biosimilar analytical similarity follows FDA/EMA biosimilar guidance. Endotoxin: USP ⟨85⟩/⟨86⟩. (Instructor: confirm current biosimilar analytical-similarity expectations.)
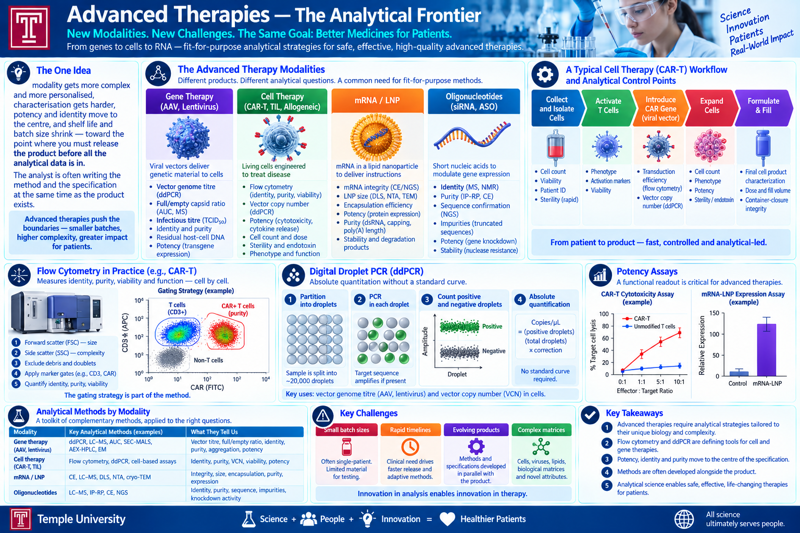
4 - The Analytical Frontier — Advanced Therapies
The analytical frontier, taught with its two defining instruments in full: flow cytometry (principles, panel design, gating, and its use for CAR-T identity/purity/potency) and ddPCR (vector genome titre, vector copy number) — plus gene therapy (AAV, full/empty capsid), mRNA-LNP, oligonucleotides, and NGS. Where batch size shrinks toward one and the analyst defines the method and the specification at the same time as the product.
This section fills in the advanced therapy column of the modality landscape table above. Large molecules were a population of one designed molecule. Advanced therapies push further: the “product” can be a virus, a strand of mRNA inside a lipid particle, or a single patient’s own cells — and the batch can be one.
The one idea
As a modality gets more complex and more personalised, characterisation gets harder, potency and identity move to the centre, and shelf life and batch size shrink — toward the point where you must release the product before all the analytical data is in. The analyst is often writing the method and the specification at the same time as the product exists.
Flow cytometry, in practice
Flow cytometry is the defining instrument of cell therapy, and it’s worth understanding mechanically, not just as a table entry — Week 9 gives it the full technique-lecture treatment (instrumentation, controls, and its reach beyond cell therapy); this is the CAR-T-specific application:
The principle. Cells in suspension flow single-file past a laser. Each cell scatters light (forward scatter ≈ size, side scatter ≈ granularity/complexity) and, if labelled with fluorescent antibodies or dyes, emits at specific wavelengths — measured cell by cell, thousands per second.
Panel design. Each fluorophore needs a distinct enough emission to be resolved from the others (spectral overlap is corrected by compensation or, in newer spectral cytometers, unmixing algorithms); a panel is built around the specific surface markers (CD antigens) that define the cell population of interest.
Gating. Data is filtered sequentially — first to exclude debris and doublets, then to select the population of interest by marker combination — and the order and logic of the gates is part of the method, not an analysis afterthought; two analysts gating the same raw data differently can report different results from identical instrument output.
What it measures for CAR-T:identity and purity (percentage of cells expressing the target CD markers), viability (live/dead stains), transduction efficiency (percentage expressing the introduced CAR construct), and — via a functional assay read out on the cytometer — a component of potency.
ddPCR, in practice
Digital droplet PCR partitions a sample into tens of thousands of nanoliter droplets, runs PCR in each independently, and counts how many droplets are positive versus negative for the target sequence — turning a continuous amplification signal into absolute molecule counts, with no reference standard curve required.
Vector genome titre — for AAV and lentivirus, the absolute count of vector genomes per mL, the number that anchors dose.
Vector copy number (VCN) — for transduced cells, how many copies of the therapeutic gene integrated per cell; too low and there’s insufficient expression, too high raises a genotoxicity concern (insertional mutagenesis).
Why ddPCR over qPCR here: absolute quantitation without a standard curve matters when reference materials are scarce or don’t yet exist — exactly the advanced-therapy situation.
The modalities and their control
Modality
Made by
Characteristic analytical panel
Gene therapy (AAV, lentivirus)
Transient transfection or packaging cell lines; downstream chromatography
Vector genome titre (ddPCR), capsid identity (LC–MS), full/empty capsid ratio (AUC, charge-detection MS, AEX-HPLC, cryo-TEM), infectious titre (TCID50), aggregation (SEC-MALS, AUC), residual host-cell DNA / plasmid / helper functions, replication-competent virus, potency (transgene expression and function)
Flow cytometry (above); vector copy number (ddPCR, above); potency (cytotoxicity, cytokine release); rapid sterility and endotoxin; cell count and dose
mRNA / LNP
In-vitro transcription → LNP formulation
mRNA integrity (CE / on-chip electrophoresis), 5′ cap and poly(A) tail analysis (LC–MS), dsRNA impurity, encapsulation efficiency and mRNA content (RiboGreen), lipid identity and quantitation (HPLC-CAD, LC–MS), particle size / PDI (DLS), zeta potential, in-vitro expression potency
Oligonucleotides (ASO, siRNA)
Solid-phase synthesis
The bridge between small and large: IEX- and RP-HPLC, LC–MS for identity and sequence-related impurities (n−1, n+1, depurination), CE
The recurring problems
Potency, again — but worse. For a living or self-assembling product, potency is central and hard: a cell-therapy cytotoxicity assay or an AAV transgene-function assay carries large variability, and there is often no validated reference material.
Identity of an assembly. When the “molecule” is a capsid carrying a genome, or a lipid particle carrying mRNA, identity is a set of orthogonal reads, not one spectrum — extending the native-MS discussion to whole viral particles.
Release before the data. A 14-day sterility test does not fit a 3-day autologous product — hence rapid microbial methods (rapid sterility, ATP bioluminescence, NAT-based mycoplasma) and, sometimes, conditional release with follow-up.
NGS as the new cross-cutting tool. Next-generation sequencing now does vector and plasmid identity/integrity, mRNA sequence confirmation, cell-line characterisation, and adventitious-agent detection — increasingly replacing in-vivo assays.
The frameworks are still forming. FDA (OTP) and EMA (ATMP / CAT) guidance, and the accelerated pathways these products often use, are evolving faster than the compendia — a lesson about working on a moving regulatory target that the chemometrics/AI week develops later in the term.
Where the analyst sits
With almost no reference materials, forming guidance, a batch size that can be one, and a clock that can be days, the analyst on an advanced therapy is doing the whole of Week 1 at once: choosing what to measure, developing the method, setting the specification, and defending all three. It is judgment under maximum uncertainty, and it is the STEAM “A” with the training wheels off.
On the job
Flow cytometry gating is one of the first places a new hire’s independent judgment shows up on a report — expect your gating scheme to be reviewed by someone more senior before your first result goes on a batch record.
If you can read a ddPCR report and explain why it doesn’t need a standard curve the way qPCR does, you’re ahead of most new hires walking into a cell-and-gene-therapy lab.
“Release before the data” is not a corner being cut — it’s a defined, validated pathway with its own paperwork (conditional release, follow-up commitments); know where to find that paperwork before you need it.
Reference materials you’d expect to just exist (a certified AAV capsid standard, a certified CAR-T potency standard) often don’t — part of the job is knowing how a lab qualifies its own in-house reference material when nothing external exists.
For discussion
An AAV lot has a full/empty capsid ratio just outside spec, but infectious titre and potency are both in range. Would you release it? What would you want to know first?
Two analysts gate the same flow-cytometry raw data differently and get different purity numbers. Whose is “right,” and how would a lab prevent this in practice?
A CAR-T cytotoxicity assay has a %CV of 30% and there is no certified reference material. How do you set a defensible specification anyway?
NGS can confirm mRNA sequence, detect adventitious agents, and characterise a cell line. What does it not tell you that a targeted assay still would?
Source note. Gene- and cell-therapy analytics follow USP ⟨1046⟩/⟨1047⟩, the emerging AAV and cell-therapy chapters, and FDA OTP and EMA ATMP guidance; flow cytometry follows standard cytometry references (Shapiro, Practical Flow Cytometry) and USP ⟨1027⟩; ddPCR follows the digital-PCR literature. mRNA-LNP follows the vaccine and mRNA-therapeutic analytical literature; oligonucleotides follow the OBP/USP oligonucleotide work. Rapid microbial methods follow USP ⟨1071⟩/⟨1223⟩ and Ph. Eur. 5.1.6 / 2.6.27. (Instructor: this field moves monthly — confirm the current guidance set; a live flow-cytometry gating demo, even on public example data, lands far better than the table alone.)